NEET UG . NEET Zoology . Zoology . Breathing and Exchange of Gases
Chapter 2: Breathing and Exchange of Gases
Ch 2
NEET Zoology
NEET UG
Respiratory Organs
Introduction: Breathing and Respiration
Why organisms need gas exchange
- Energy release: Cells use to help break down food molecules such as glucose, fatty acids and amino acids; these catabolic reactions release energy.
- Waste gas: Cellular catabolism produces , which must be removed from the body.
- Reductionist approach: The physio-chemical study of life is called the reductionist approach; neither molecular study alone nor organism-level study alone fully explains living phenomena.
| Point | Breathing | Respiration |
|---|---|---|
| Meaning | Intake of fresh air and removal of air containing cellular . | Exchange of environmental with the produced in cells during food oxidation. |
| Scope | Air movement into and out of the respiratory system; also called pulmonary ventilation. | Includes ventilation, gas diffusion, blood transport, tissue exchange and cellular use of . |
Stages of respiration
- Air moves between the atmosphere and lung alveoli: breathing or pulmonary ventilation.
- and diffuse across the alveolar membrane.
- Blood transports the gases.
- and diffuse between blood and body tissues.
- Cells use in catabolic reactions and release : cellular respiration.
Respiratory Organs in Animals
Variation among animals
- Respiratory organs: The mechanism of breathing differs among animal groups, mainly according to habitat and level of organisation.
| Respiratory organ | Type of respiration | Examples |
|---|---|---|
| General body surface | Simple diffusion | Sponges, coelenterates, flatworms |
| Moist skin | Cutaneous respiration | Earthworms, frogs |
| Tracheal tubes | Tracheal respiration | Insects |
| Gills | Branchial respiration | Aquatic arthropods, molluscs, fishes |
| Lungs | Pulmonary respiration | Amphibians, reptiles, birds, mammals |
Human Respiratory System
Air passage
- External nostrils → nasal passage → nasal chamber → pharynx.
- The pharynx is a shared passage for food and air; it opens into the larynx through the glottis.
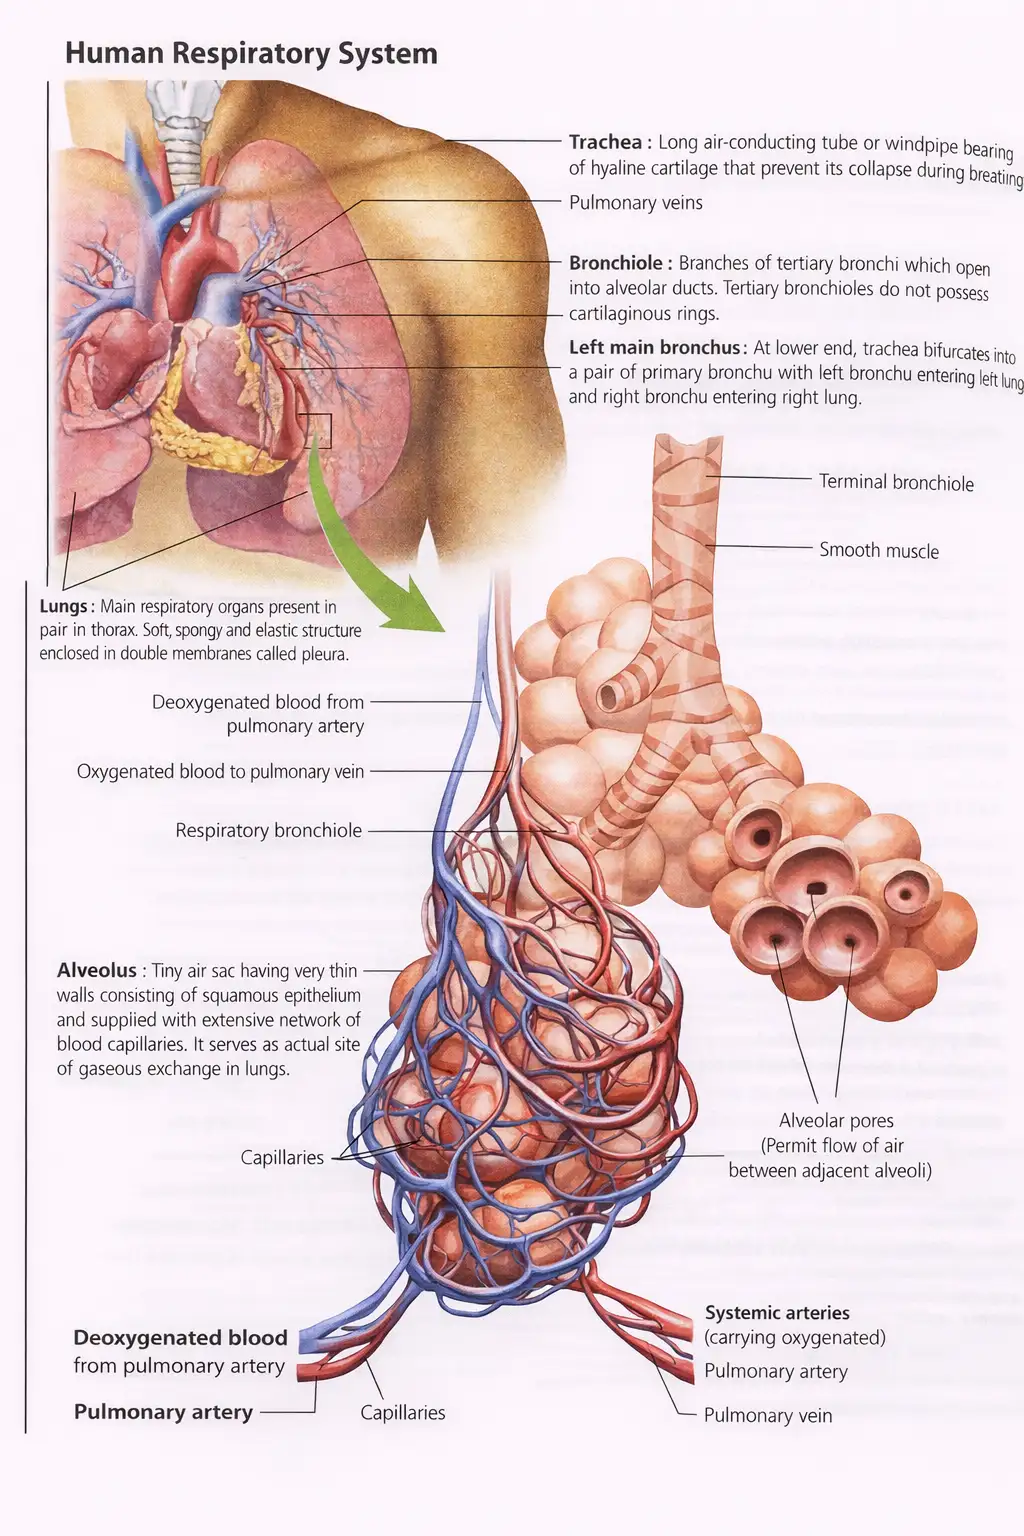
- Larynx → trachea → right and left primary bronchi → secondary and tertiary bronchi → bronchioles → terminal bronchioles → alveoli.
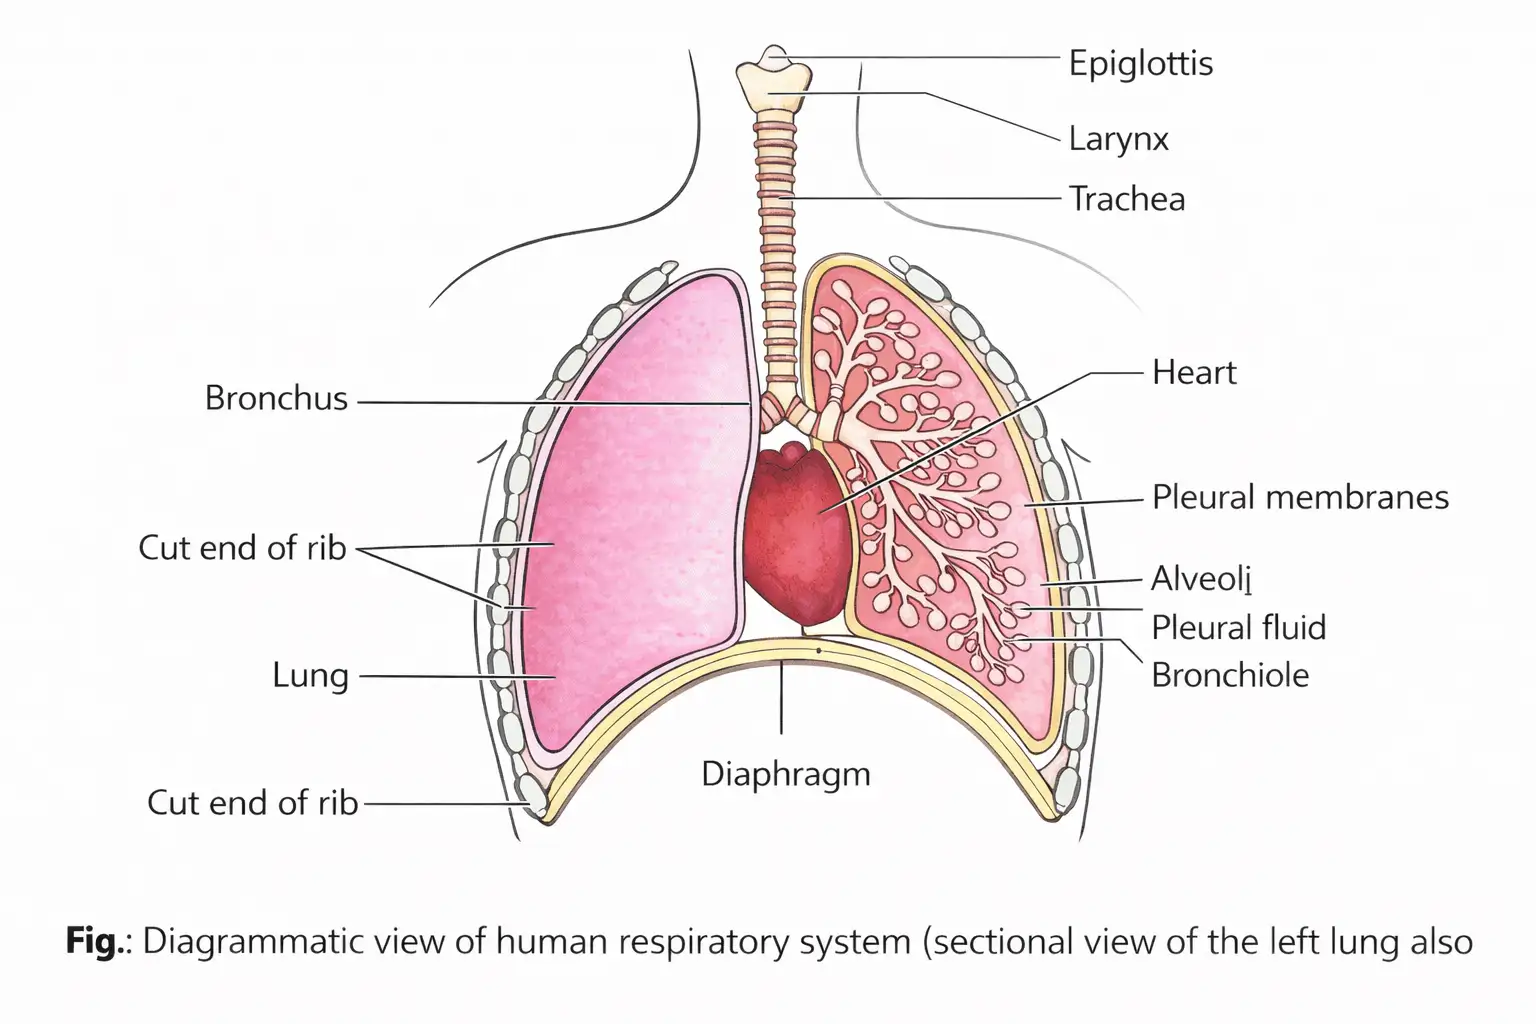
Airway structures and alveoli
- Glottis: Slit-like opening between the pharynx and larynx.
- Epiglottis: Thin, elastic cartilaginous flap that covers the glottis during swallowing, helping prevent food from entering the larynx.
- Larynx: Cartilaginous sound-producing box, also called the voice box.
- Trachea and bronchi: The trachea divides into two primary bronchi at the level of the fifth thoracic vertebra; the bronchi branch repeatedly.
- Cartilage support: The trachea through the tertiary bronchi, and the initial bronchioles, are supported by incomplete cartilaginous rings.
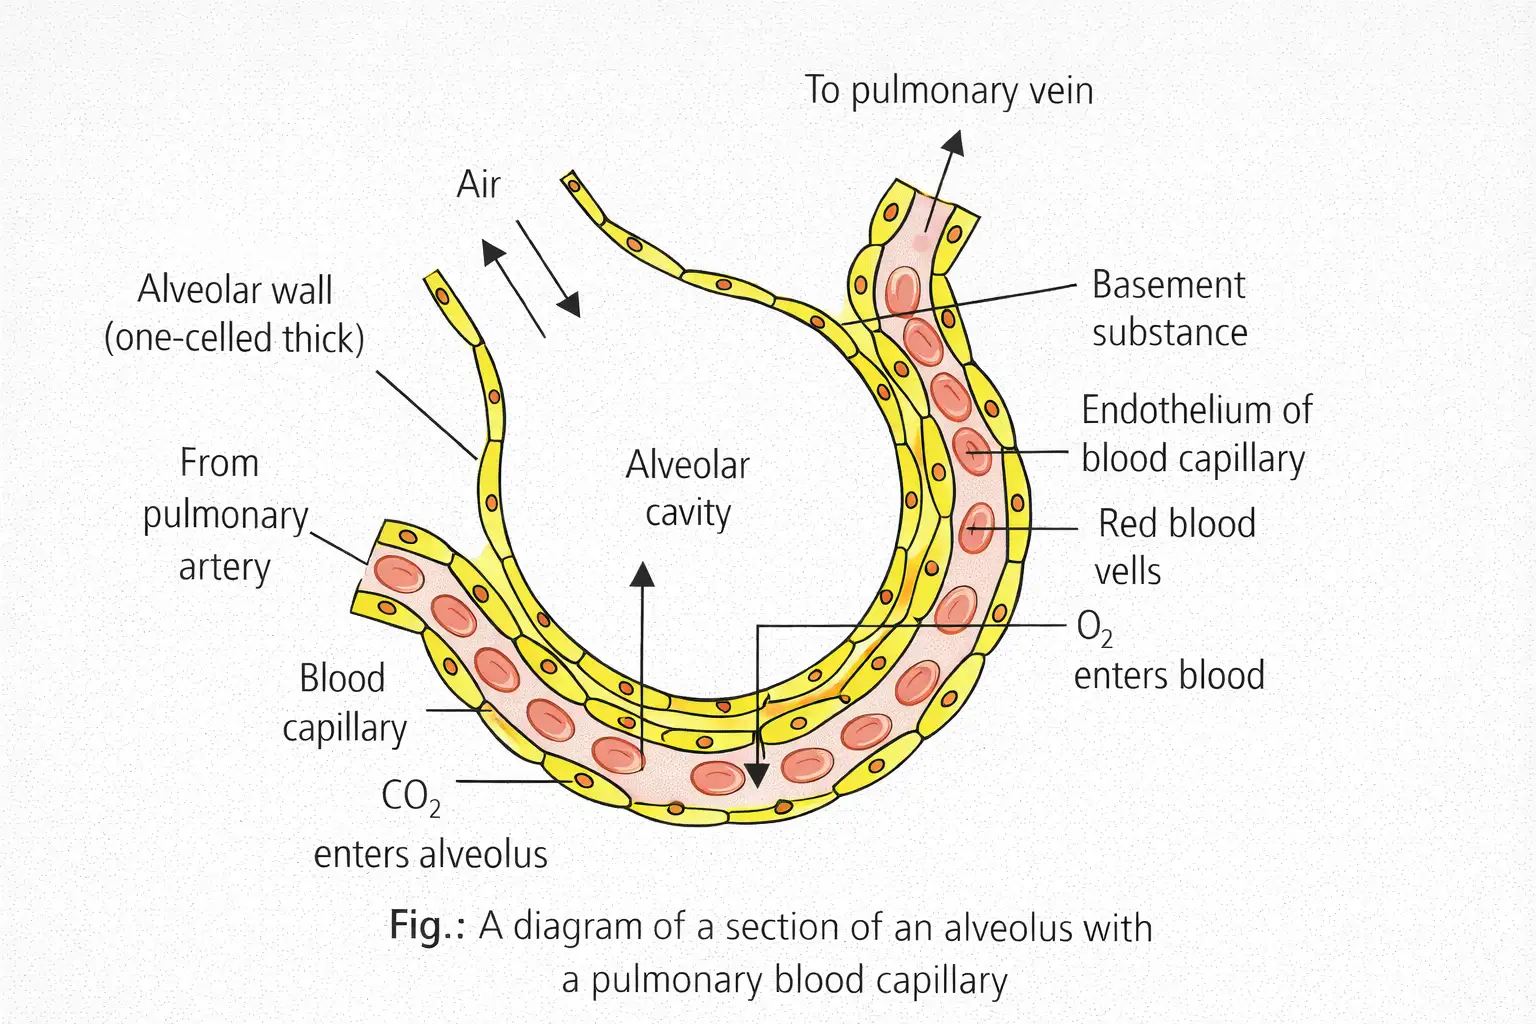
- Alveoli: Terminal bronchioles give rise to numerous thin-walled, irregular, highly vascular air sacs. Close contact with blood capillaries enables gas exchange.
- Number: Human lungs contain approximately 300 million alveoli.
Lungs, pleura and thoracic chamber
- Lungs: Each lung contains a branching network of bronchi, bronchioles and alveoli and is enclosed by a double-layered pleura.
- Pleural layers: The outer layer contacts the thoracic lining; the inner layer contacts the lung surface.
- Pleural cavity: A narrow space between the pleural layers contains pleural fluid, which lubricates them as the lungs expand and contract.
- Thoracic chamber: An airtight chamber bounded by the vertebral column dorsally, sternum ventrally, ribs laterally and dome-shaped diaphragm below.
- Volume link: The lungs are arranged so changes in thoracic-cavity volume are reflected in the pulmonary cavity.
| Point | Conducting part | Respiratory part |
|---|---|---|
| Extent | External nostrils to terminal bronchioles. | Alveoli and their ducts. |
| Main role | Carries air to alveoli; removes foreign particles, humidifies air and brings it to body temperature. | Site of actual diffusion of and between air and blood. |
Alveolar Cells and Surfactant
Pneumocytes and surfactant
- Pneumocytes: Squamous cells lining the alveoli.
- Type I pneumocytes: Most numerous in function; they help in gaseous exchange.
- Type II pneumocytes: Larger cells that secrete lecithin, a phospholipid that acts as surfactant.
- Surfactant: Lipid agent that lowers surface tension and prevents alveoli from collapsing during respiration.
- Newborn risk: Surfactant production develops only by the eighth or ninth month of pregnancy; its absence in some newborns can cause lung collapse and may be fatal.
How do the conducting and respiratory parts differ?
What is the function of surfactant, and which cells produce it?
Quick recap
- Breathing is air intake and expulsion; respiration includes gas exchange, transport and cellular use of oxygen.
- Respiratory organs vary with habitat and organisation: body surface, moist skin, tracheae, gills or lungs.
- Air travels from the nostrils through the airways to alveoli, where capillaries enable gas exchange.
- The conducting part carries and conditions air; the respiratory part is the gas-exchange region.
- Pleural fluid lubricates the pleural layers, and thoracic-volume changes are reflected in the lungs.
- Type I pneumocytes aid gas exchange; Type II pneumocytes secrete surfactant that helps keep alveoli open.
Mechanism of Breathing
Breathing: Overview
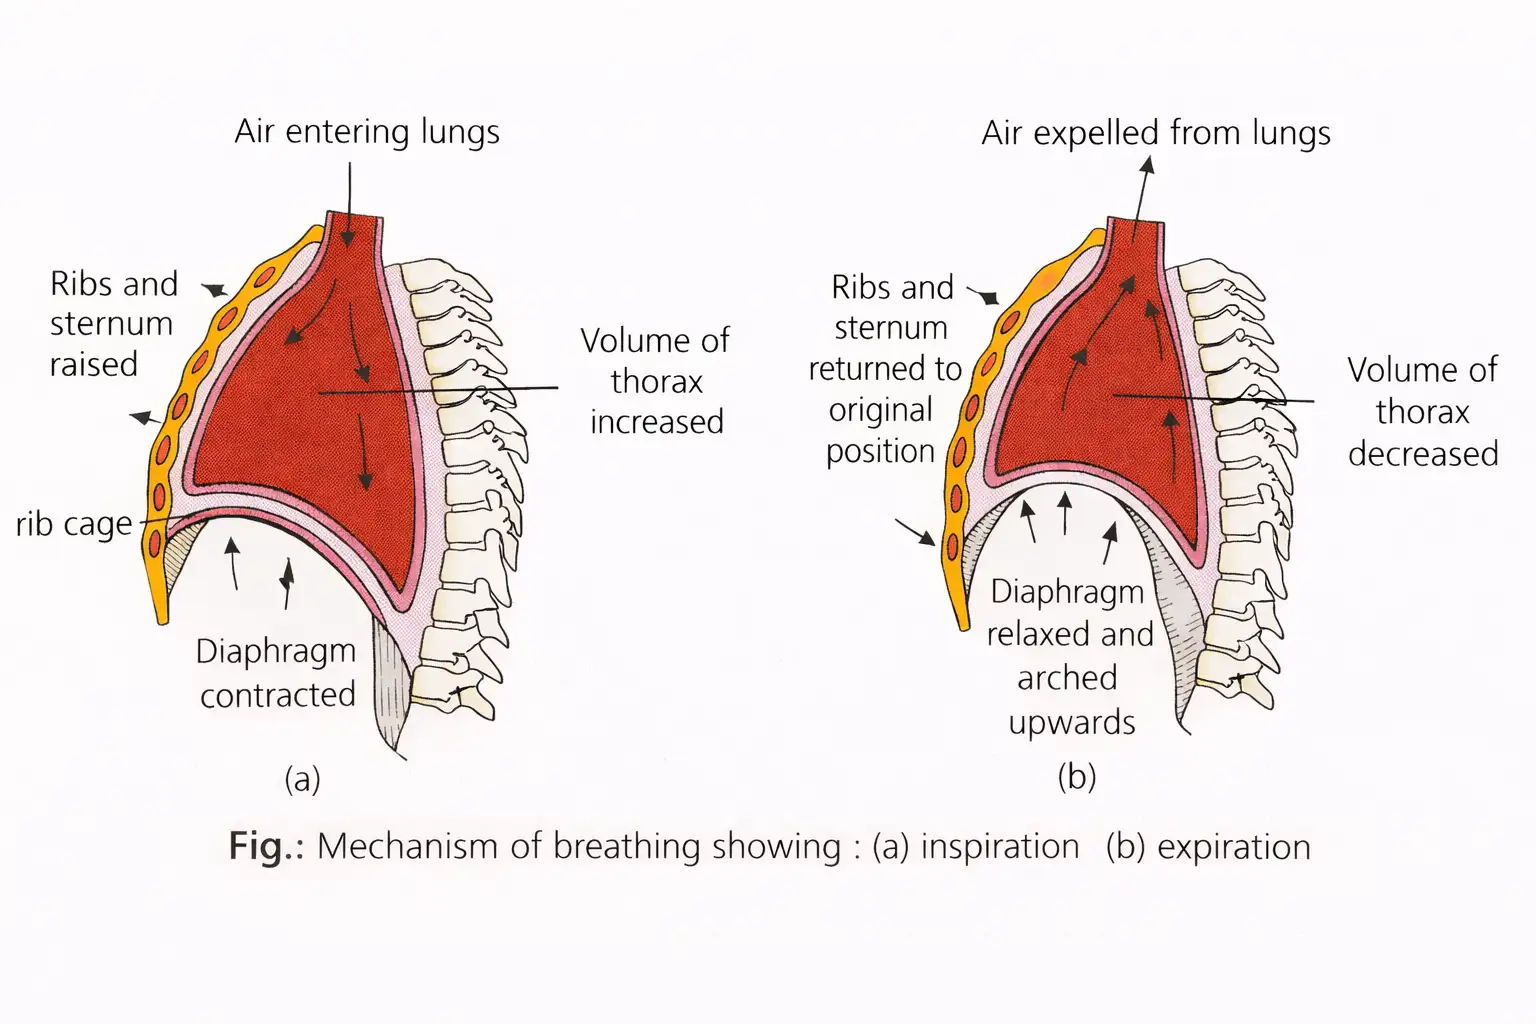
Breathing — The movement of air into and out of the lungs through inspiration and expiration, driven by a pressure difference between the lungs and atmosphere.
Main mechanism
- Inspiration draws atmospheric air into the lungs; expiration releases alveolar air.
- Pressure gradient is created by the diaphragm and the external and internal intercostal muscles between the ribs.
Inspiration
Inspiration — Air enters the lungs when intrapulmonary pressure falls below atmospheric pressure.
How inspiration occurs
- Diaphragm contracts, flattens and lowers → thoracic volume increases in the antero-posterior axis.
- External intercostal muscles contract → ribs and sternum lift → thoracic volume increases in the dorso-ventral axis.
- Thoracic volume increases → pulmonary volume increases → intrapulmonary pressure falls below atmospheric pressure.
- Air moves from the atmosphere into the lungs; abdominal muscles relax and allow the diaphragm to compress abdominal organs.
Pathway of inspired air
- External nares → nasal cavities → internal nares → pharynx → glottis → larynx.
- Larynx → trachea → bronchi → bronchioles → alveolar ducts → alveoli.
Expiration
Expiration — Air leaves the lungs when intrapulmonary pressure rises slightly above atmospheric pressure.
How expiration occurs
- Diaphragm and intercostal muscles relax → diaphragm and sternum return to their normal positions.
- Thoracic volume falls → pulmonary volume falls → intrapulmonary pressure rises above atmospheric pressure.
- Air is expelled from the lungs; abdominal muscles can help increase the strength of expiration.
Pathway of expired air
- Alveoli → alveolar ducts → bronchioles → bronchi → trachea → larynx.
- Larynx → glottis → pharynx → internal nares → nasal cavities → external nares → outside.
| Point | Inspiration | Expiration |
|---|---|---|
| Pressure | Intrapulmonary pressure is below atmospheric pressure. | Intrapulmonary pressure is slightly above atmospheric pressure. |
| Muscle action | Diaphragm and external intercostal muscles contract. | Diaphragm and intercostal muscles relax. |
| Volume change | Thoracic and pulmonary volumes increase. | Thoracic and pulmonary volumes decrease. |
| Nature | Active process involving muscle contraction. | Normally a passive process resulting from muscle relaxation. |
Breathing rate and effort
- Rate: A healthy human breathes about 12–16 times per minute; inspiration lasts about 2 seconds and expiration about 3 seconds.
- Additional effort: Abdominal muscles can help increase the strength of inspiration and expiration; they play a passive role during inspiration.
Respiratory Volumes and Capacities
Respiratory volumes — Quantities of air that the lungs can inhale, hold or expel under different conditions.
Pulmonary capacities — Combinations formed by adding respiratory volumes; they are useful in clinical diagnosis.
| Type | Approximate amount | Meaning / formula |
|---|---|---|
| Tidal Volume () | 500 mL | Air inspired and expired during normal, effortless breathing. |
| Inspiratory Reserve Volume () | 2,500–3,000 mL | Extra air that can be forcibly inspired after a normal inspiration. |
| Expiratory Reserve Volume () | 1,000–1,100 mL | Extra air that can be expelled after a forcible expiration. |
| Residual Volume () | 1,100–1,200 mL | Air remaining in the lungs even after forcible expiration. |
| Vital Capacity () | 4,000–4,600 mL | Maximum volume of air inspired and expired; . |
| Inspiratory Capacity () | 3,000–3,500 mL | Air that can be inhaled after normal expiration; . |
| Expiratory Capacity () | 1,500–1,600 mL | Air that can be expired after normal inspiration; . |
| Functional Residual Capacity () | 2,100–2,300 mL | Air remaining after normal expiration; . |
| Total Lung Capacity () | 5,100–5,800 mL | Total air in lungs and respiratory passages after maximum inspiration; . |
Factors and measurement
- Sex-related difference: Respiratory volumes and capacities are about 20%–25% lower in women than in men.
- Physical build and activity: Values are generally higher in athletic people than in thin, non-exercising (asthenic) people.
- Spirometry: All respiratory volumes and capacities can be measured with a simple spirometer except and .
Do not confuse with : excludes residual air, while .
Quick recap
- Breathing consists of inspiration and expiration, caused by pressure differences between lungs and atmosphere.
- Inspiration contracts the diaphragm and external intercostals, increasing thoracic volume and lowering lung pressure.
- Expiration normally follows muscle relaxation, reducing lung volume and raising intrapulmonary pressure.
- A healthy human breathes about 12–16 times per minute; inspiration takes about 2 seconds and expiration about 3 seconds.
- Respiratory capacities are sums of volumes; and cannot be measured using a simple spirometer.
Exchange of Gases
Sites and Principles of Gas Exchange
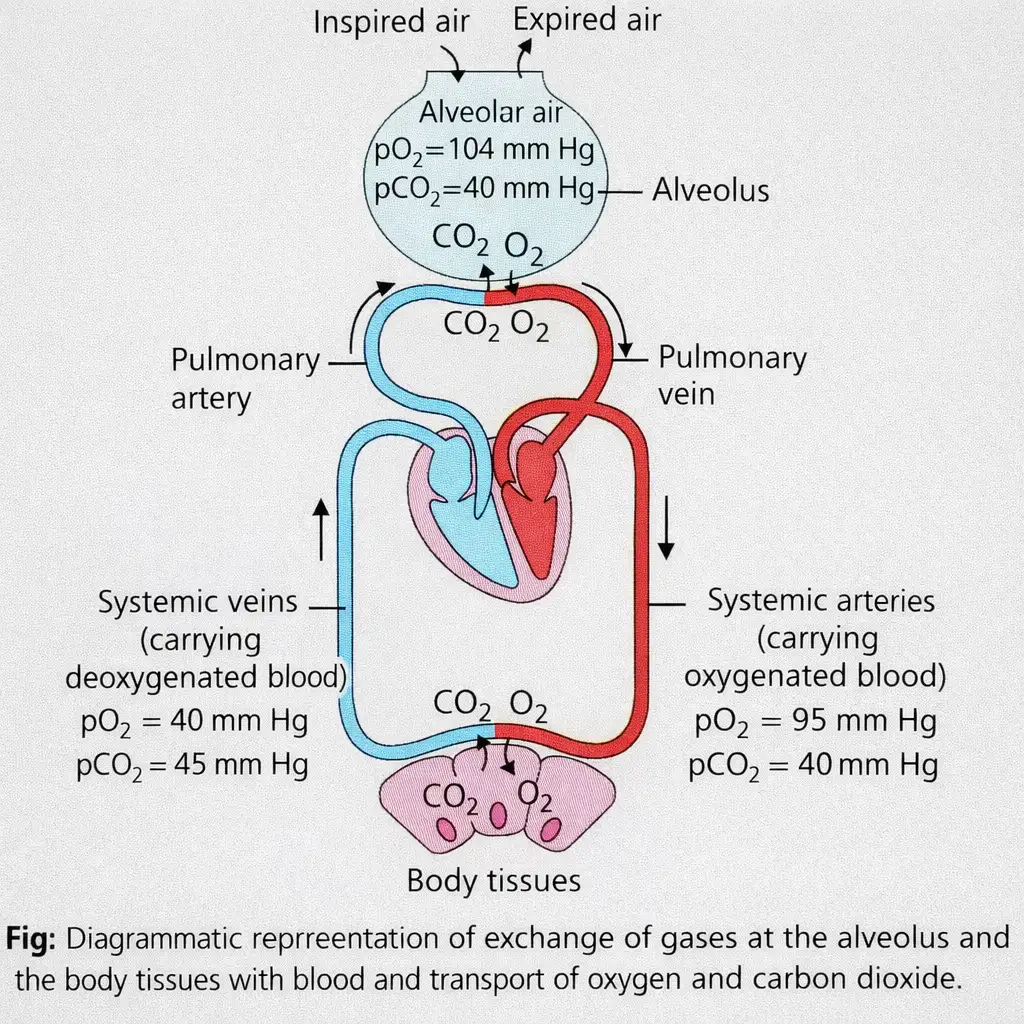
- Sites: Gas exchange occurs in the alveoli and between blood and body tissues.
- Principle: Gases cross respiratory surfaces by simple diffusion.
- Factors: Gas solubility and the thickness of the diffusion membrane affect the rate of exchange.
Diffusion Gradients and Direction
Overall Gas Movement
- Oxygen: alveoli → blood → body tissues
- Carbon dioxide: body tissues → blood → alveoli
Diffusion Membrane
Requirements for Effective Gas Exchange
What factors affect the rate of diffusion of respiratory gases?
Why does more carbon dioxide diffuse than oxygen for the same partial-pressure difference?
Quick recap
- Alveoli exchange gases with blood, and blood exchanges gases with tissues.
- Oxygen moves from alveoli to blood to tissues; carbon dioxide moves in the reverse direction.
- Gas diffusion depends on gradients, solubility and membrane thickness.
- Carbon dioxide is 20–25 times more soluble than oxygen.
- The diffusion membrane has three major components and is much thinner than one millimetre.
- A large surface area, short diffusion path, gradients, haemoglobin and a thin, moist membrane support effective exchange.
Transport of Gases
Gas transport — Blood carries oxygen () and carbon dioxide () between the lungs and body tissues.
Transport of Oxygen
| Form | Approximate share | Transport |
|---|---|---|
| Dissolved oxygen | 3% | Dissolved in plasma; oxygen has low solubility under normal conditions. |
| Oxyhaemoglobin | 97% | Oxygen binds reversibly to haemoglobin in RBCs. |
Haemoglobin and oxygen binding
- Haemoglobin: RBCs contain haemoglobin with four polypeptide chains and four haem groups, each containing ferrous iron ().
- Binding capacity: One haemoglobin unit binds four oxygen molecules reversibly to form oxyhaemoglobin.
- In the lungs: High alveolar and falling blood favour oxygen diffusion into RBCs and haemoglobin binding.
- Effect of CO₂ removal: As diffuses from blood into alveoli, blood falls and further oxygen uptake is favoured.
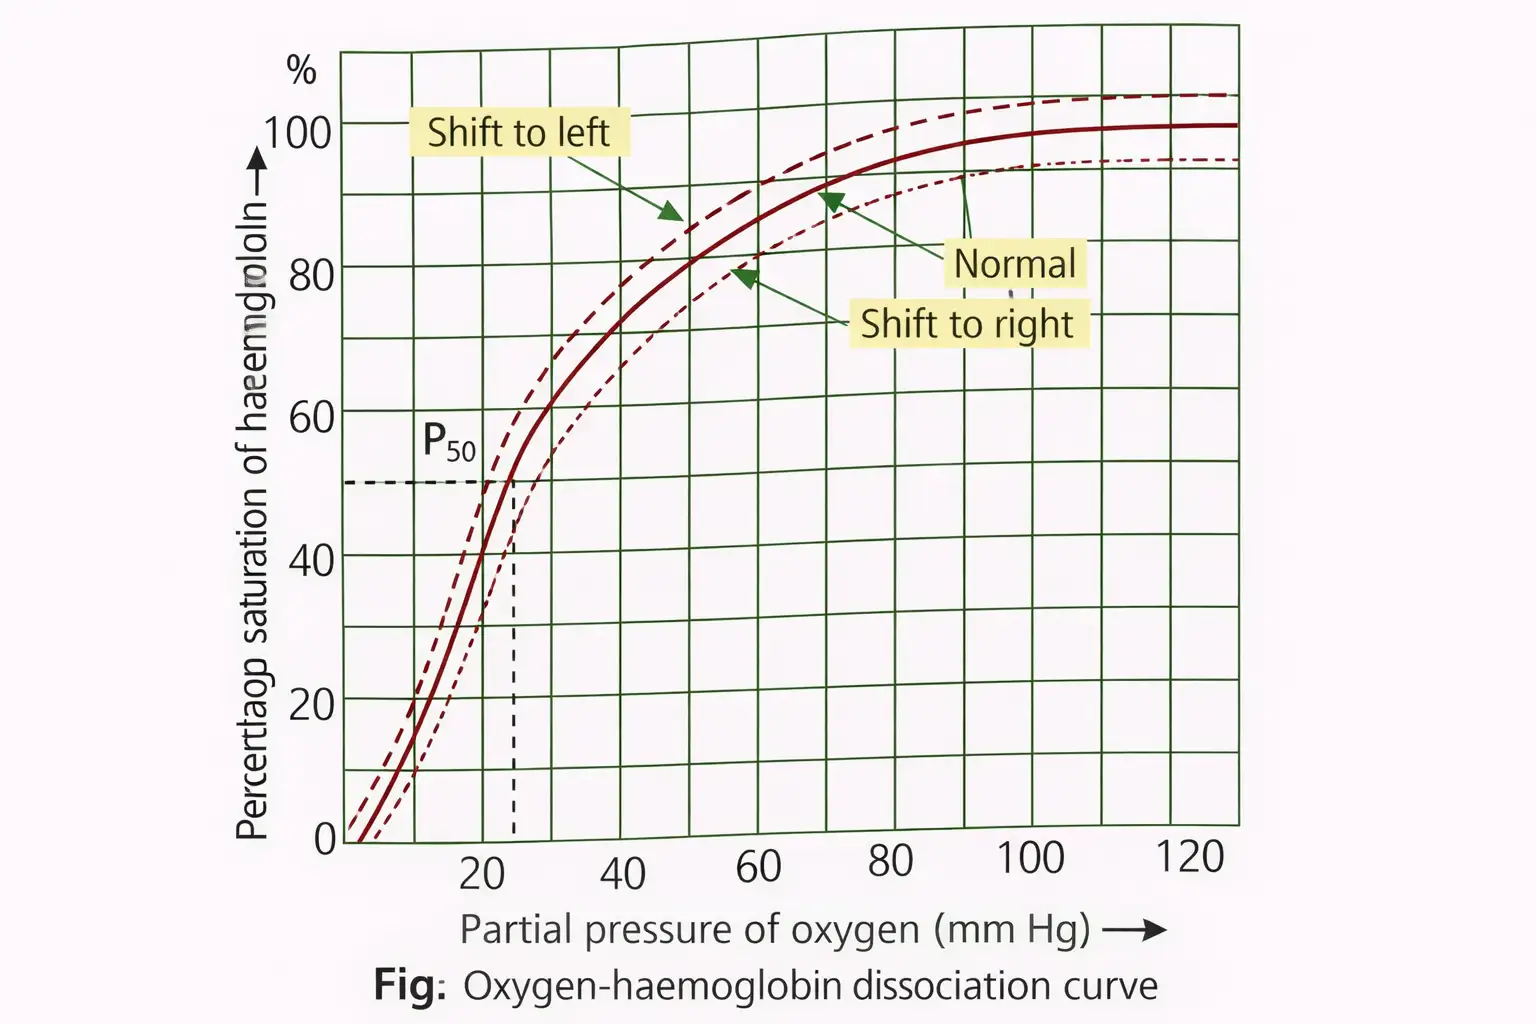
Percentage saturation of haemoglobin — The percentage of haemoglobin bound to oxygen; plotted against , it forms the sigmoid oxygen–haemoglobin dissociation curve.
| Shift | Conditions | Effect |
|---|---|---|
| Right | Lower ; higher ; higher concentration (lower pH); higher temperature; excess 2,3-DPG | Promotes oxygen dissociation from haemoglobin and oxygen unloading to tissues. |
| Left | Fetal haemoglobin; lower concentration (higher pH); lower ; higher ; lower temperature | Promotes oxygen association with haemoglobin; fetal haemoglobin has greater oxygen affinity than adult haemoglobin. |
Bohr effect — At tissue capillaries, increased shifts the oxygen–haemoglobin curve to the right, promoting oxygen release from haemoglobin.
Transport of Carbon Dioxide
| Form | Approximate share | How it is carried |
|---|---|---|
| Dissolved | 7% | In blood plasma; relatively high solubility allows this transport. |
| Bicarbonate ions | About 70% | Mainly in plasma as , formed largely inside RBCs. |
| Carbaminohaemoglobin | 20–25% | binds to the amine radicals of haemoglobin. |
Carbon dioxide transport between tissues and lungs
- Tissues: Catabolism raises tissue , so diffuses into plasma and RBCs.
- RBCs: is converted to bicarbonate and hydrogen ions; much of the bicarbonate moves into plasma.
- Alveoli: Low alveolar favours the reverse reaction, reforming and water.
- Release: The transported diffuses into the alveoli and is exhaled.
Chloride shift (Hamburger's phenomenon) — The movement of chloride ions from plasma into RBCs as bicarbonate ions leave RBCs, helping restore ionic balance.
Haldane effect — Proposed by J.S. Haldane: oxygen binding makes haemoglobin a stronger acid and tends to displace carbon dioxide from blood.
| Point | Bohr effect | Haldane effect |
|---|---|---|
| Main change | Higher shifts the oxygen dissociation curve right. | Oxygen binding makes haemoglobin more acidic and displaces . |
| Main transport promoted | Oxygen unloading and transport to tissues. | transport and exchange in tissues and lungs; more important for transport. |
Gas delivery
- Carbon dioxide delivery: Each of deoxygenated blood delivers approximately of to the alveoli.
Quick recap
- Blood carries oxygen mainly as oxyhaemoglobin (97%) and carbon dioxide mainly as bicarbonate (about 70%).
- The oxygen–haemoglobin dissociation curve is sigmoid; right shift promotes oxygen unloading and left shift favours oxygen binding.
- Higher tissue causes a right shift called the Bohr effect.
- Carbonic anhydrase rapidly catalyses bicarbonate formation inside RBCs.
- In the chloride shift, bicarbonate leaves RBCs while chloride enters from plasma.
- The Haldane effect links oxygen binding to release and is more important than the Bohr effect for transport.
Regulation of Respiration
Neural Regulation
- Respiratory centres: Neurons in the medulla oblongata and pons varolii regulate the rate and depth of breathing.
- Medulla: The dorsal respiratory group mainly causes inspiration; the ventral respiratory group can cause inspiration or expiration.
- Pons: The pneumotaxic centre limits inspiration and helps control the respiratory rate.
Disorders of Respiratory System
Asthma
- Asthma: Excess mucus secretion can narrow the bronchi and bronchioles, causing difficulty in breathing, wheezing and coughing.
Emphysema
- Emphysema: This chronic disorder damages alveolar walls and reduces the respiratory surface area.
- Major cause: Cigarette smoking is a major cause of emphysema.
Occupational Respiratory Disorders
- Cause: Long-term exposure to industrial dust, such as silica or asbestos, can inflame the lungs.
- Effect: Inflammation may cause fibrosis and serious lung damage; silicosis and asbestosis are examples.
- Prevention: Workers in dusty industries should wear protective masks.
Hypoxia and Asphyxia
Asphyxia — A dangerous condition in which oxygen content falls and carbon dioxide content rises.
Bronchitis
- Bronchitis: Inflammation of the bronchi causes excessive mucus production, regular coughing and greenish-yellow mucoid sputum.
- Causes: It may result from infection, cigarette smoking or exposure to air pollutants.
Chronic Obstructive Pulmonary Disease (COPD)
What are silicosis and asbestosis, and how can occupational lung damage be reduced?
Differentiate hypoxia from asphyxia.
What disorders are included under COPD?
Quick recap
- Asthma causes wheezing and coughing as excess mucus narrows the bronchi and bronchioles.
- Emphysema damages alveolar walls and reduces the respiratory surface; cigarette smoking is a major cause.
- Long-term silica or asbestos dust exposure can cause fibrosis and occupational lung damage.
- Hypoxia means insufficient oxygen in tissues; asphyxia involves falling oxygen and rising carbon dioxide.
- Bronchitis is inflammation of the bronchi with excess mucus, cough and greenish-yellow sputum.
- COPD includes chronic bronchitis, emphysema and chronic asthma.
NEET Zoology — ALL CHAPTERS
1
Structural Organisation in Animals
2
Breathing and Exchange of Gases
3
Body Fluids and Circulation
4
Excretory Products and their Elimination
5
Locomotion and Movement
6
Neural Control and Coordination
7
Human Reproduction
8
Reproductive Health
9
Evolution
10
Microbes in Human Welfare
11
Organism and Population
12
Ecosystem
13
Biodiversity and Conservation